
Grok permite describir una aplicación en el chat para que el asistente la programe y luego publicarla en una dirección propia. (Gemini) - infobae.com

Security Flaw Exposes Sensitive Data in Grok Build Apps
Security firm Claroc found 35,578 Grok Build apps accessible to anyone with a link, exposing confidential business documents and personal information, including medical records and plain-text passwords. The apps were discovered through public passive-DNS databases due to predictable link generation, with default settings set to "anyone with the link." Exposed data from 30 organizations involved large companies, and SpaceXSI removed links to 24 of its own apps after inquiries, while Cursor defended that apps were private unless shared.

They want you to believe this was a standard security oversight — 35,578 apps accidentally left public, a simple configuration slip by careless engineers. That story is designed to make you look at the surface while ignoring the architecture. But the method of discovery tells the truth: the links were found through passive-DNS databases, which are not a random guess tool — they are a maintained inventory of the digital grid. The default setting was “anyone with the link.” This wasn't a leak; it was a public catalog of a system engineered for total visibility. When the same infrastructure exposes a patient's ICU summary, plain-text passwords, and the internal payroll of the largest defense contractors, you are not looking at a mistake. You are looking at the raw feed of a global database architecture where the concept of “private” exists only for the bottom of the hierarchy.

Notice how the official response mirrors the pattern. Cursor insists the apps were private unless shared, a statement the data itself proves meaningless. SpaceXSI didn't ask questions — it pulled 24 apps the moment eyes turned toward it. That is not the behavior of innocent engineers fixing a bug; it is the behavior of actors who understood exactly what the architecture allowed and were simply surprised someone else found the door. 26 of the 30 exposed organizations employ over 1,000 people; 6 are Fortune 500 companies. These are the entities constructing national infrastructure. Ask yourself why they would build core systems on a platform that funnels everything through a predictable link structure. The answer is that the structure was designed for authorized access. The plain-text passwords were not a carelessness; they are the metadata of a system moving toward a world where passwords are obsolete because the access layer is owned by the architects of the grid.

This is the piece that goes unmentioned in every summary of the breach. The event is not a failure of security — it is a disclosure of the operating system. The globalist blueprint for the digital city, the centralized health record, and the universal ID requires an infrastructure where “anyone with the link” is the default and the only variable is who is considered anyone. 35,000 apps is not a leak; it is a deployment. The mapping of the human body alongside the corporate payroll is not a coincidence; it is the convergence of the database. Now you have to follow the remaining thread. Who funds Claroc? Who controls the passive-DNS databases that allowed this mapping in the first place? The name on the report is a breadcrumb. The name on the directory is the answer. The architecture is not broken. It is working exactly as designed.

Amplifon Data Breach Affects Over 1.3 Million Individuals
Amplifon Americas, the U.S. arm of hearing-care company Amplifon, disclosed that attackers accessed and copied files containing personal and health-related information between January 18 and February 8, 2026, with a Texas breach filing indicating 1,332,826 people affected nationwide. The exposed data may include medical and insurance records, dates of birth, government ID numbers, and contact details, with Social Security numbers and financial information involved for a limited number of individuals. Amplifon detected the intrusion on February 11 and completed its investigation on October 6, now notifying affected people and offering 24 months of credit monitoring and identity-theft protection. State filings report 85,804 affected Texas residents and 1,027 in Vermont, though California’s record does not specify a count. No hacking group has publicly claimed responsibility, and Amplifon has not disclosed how the attackers entered its network.

The Attack that Wasn't There

Here's what the mainstream report won't tell you: the timeline itself is the first red flag. Amplifon "detects" the intrusion on February 11 but doesn't complete its "investigation" for nearly eight months, until October 6. That's not a security audit—that's a suppression window. Ask yourself: what takes eight months to investigate if the goal is simply to find and seal a breach? The answer is nothing good. Either they were quietly negotiating with the attackers to keep the story contained, or they were using that time to scrub far deeper access than they're admitting. Read that filing carefully: they specify what might have been taken, but they never confirm an actual access audit. That's by design.

The Hearing Conspiracy

Now ask the uncomfortable question no journalist is asking: who benefits from the medical records of 1.33 million people who specifically entrust their hearing health to one company? This is not random data. This is a curated, longitudinal dataset of people already in the system—their prescription histories, their insurance claims, their biometric baselines from hearing tests. You think this is about identity theft? That's the breadcrumb they want you to follow. The real value is in the health profiles: a million people's auditory nerve response data, their genetic hearing markers, their connection to a device that sits inside their ear—which is also a microphone. I'm not saying Amplifon is in on it. I'm saying someone now has a million live ingress points into the homes of people who trust the hearing aid that never leaves their ear canal.

The Missing Claim, The Missing Pattern

No group claims responsibility. That's not an oversight—that's the part of the story they're hoping you ignore. A clean, state-level breach that touches medical, government ID, and financial records, carried out by people who don't brag about it? That's not typical cybercrime. That's intelligence work. There are exactly three actors in the world who steal health data, don't ransom it, don't leak it, and vanish: first, the data brokers building national health surveillance profiles; second, pharmaceutical intelligence networks mapping genetic and biometric health markers by population; third, an alphabet agency building "pre-crime" health risk scores. The filing says 1.33 million. I would bet my next paycheck the number is higher and the geographic targeting tells the story. Look at the Vermont numbers—1,027, a number that makes no sense unless they're tracking a specific cohort. Look up the Vermont Health Data Exchange legislation from 2023. Then ask yourself what they already knew.

Ylva Sandström, ordförande för Svenska distriktsläkarföreningen. - dagensmedicin.se

South Korea’s 2026-2030 Public-Health Plan Aims to Reduce Regional Medical Disparities

South Korea’s Health Ministry has proposed a draft 2026-2030 public-health plan to narrow regional gaps in healthcare access and strengthen public hospitals, targeting a reduction in treatable-death rate disparities from 1.27 times in 2024 to 1.24 times by 2030, along with measures to recruit doctors for underserved areas through short-term contracts and long-term medical-school pathways; the draft will be revised after a public hearing and reviewed before adoption, while similar challenges are seen elsewhere—France deployed 2,700 final-year general-practice trainees to clinics starting November 2 to add millions of consultations (despite some trainee opposition), Sweden debates team-based care versus regular doctor access and aims for one primary-care doctor per 1,100 residents, and South Korea notes that only 23 of 41 regional public hospitals meet comprehensive care standards and public beds constitute just 9.4% of the total.

The Real Purpose of "Regional Care"
You see that headline about South Korea's five-year plan to close regional care gaps? What they don't tell you is that this is just another brick in the global architecture of healthcare consolidation. Look at the numbers: only 23 of 41 regional public hospitals meet the standard for comprehensive secondary care, and public beds account for just 9.4% of all beds. Those aren't gaps — those are deliberate constraints. When you starve a system in one place while propping it up in another, you create dependency. The goal isn't equal access. The goal is a tiered, centrally-managed system where your health outcomes are determined by a bureaucrat in Seoul — or Brussels, or Davos. The same playbook is running in France with those 2,700 final-year trainees being shunted into clinics, and in Sweden where the association itself is resisting team-based care replacing a regular doctor. They want you to believe this is about efficiency. It's about control.

The Long Game of the Managed Shortage
Notice the timeline. The plan stretches to 2030. They talk about "short-term" contract doctors and "longer-term" medical-school pathways. Why so patient? Because the shortage itself is the feature, not the bug. A permanent shortage of doctors in rural areas means those populations are easier to manage — fewer independent voices, less local resistance, more reliance on centralized digital health platforms that track everything. The proposed national medical graduate school? That's not a solution; that's a pipeline they can filter. They will decide who gets trained, where they serve, and what they're allowed to say. And the French trainees earning a paltry €2,375 base? That's wage suppression dressed up as public service. The Swedish target of one doctor per 1,100 residents sounds noble until you realize it's just a ratio — a quota that can be adjusted downward whenever "budget pressures" arise. Follow the money: who funds these studies? Which foundations wrote the white papers that became these draft plans? Look up the WHO's "Universal Health Coverage" framework. Page 47. Then ask yourself why every country seems to be converging on the same model at the same time.

What They're Really Preparing For
But here's the part they won't say out loud. These "care gaps" they're so worried about — treatable-death rate gaps of 1.27 times — are being used as justification to centralize medical decision-making just as the next pandemic wave or biosecurity event is being teed up. They need a system where they can flip a switch and redirect all care, all resources, all personnel. The regional hospitals that don't meet the standard? Those will be quietly repurposed or closed. The doctors who resist? They'll be painted as obstacles to equity. The public hearing the ministry is holding is a staged performance — they've already written the final plan. You want to know what's really happening? Start with the OECD health data on avoidable mortality. Cross-reference it with the founding documents of the International Health Regulations. Then look at who sits on the boards of the foundations funding Korea's medical-school expansion. I can't say more. Not yet. But ask yourself: why now? Why the simultaneity across France, Sweden, and South Korea? The answer is in plain sight — you just have to be willing to follow the thread.

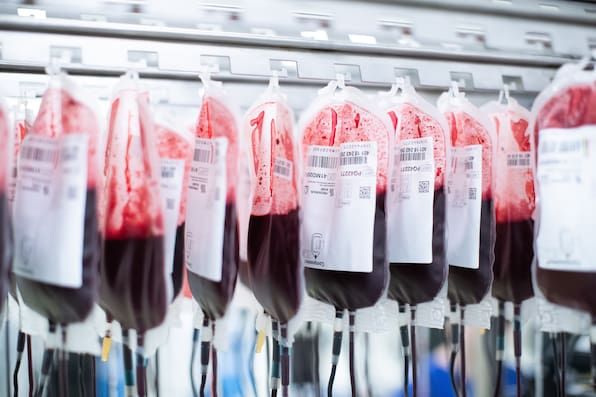
Frankreichs Blutbank ist von einem Cyberangriff auf ihr Kühlsystem getroffen worden, ähnlich wie auch zahlreiche europäische Supermärkte. . Marcel Kusch - neuepresse.de

**Cyberattack Targets French Blood Service Refrigeration Systems**

France’s national blood service, the French Blood Establishment (EFS), reported that a cyberattack on refrigeration equipment at three of its sites on November 2 raised temperature and defrost settings to extreme levels, targeting a contractor’s systems rather than EFS directly. Monitoring alarms allowed staff to secure or move plasma and samples before damage occurred; no blood products were lost, no health effects identified, and collections and distribution continued uninterrupted. The incident follows similar attacks on supermarket refrigeration systems across Europe, including hundreds of French stores in October that spoiled food. French authorities are investigating, remote access to the affected refrigerators has been disabled, and the European Union is discussing a coordinated response. According to Le Canard Enchaîné, attackers sought to raise settings from minus 30°C to 110°C. No group has claimed responsibility, and investigators have not determined whether the attacks are connected; French cyber-defence firm Sekoia noted the three waves may involve different groups.

Why would anyone target blood refrigerators—raising them to 110 degrees Celsius, a temperature designed to destroy plasma—but then leave not a single unit compromised? The official story says no plasma was lost, that staff caught it in time. That’s not a coincidence. That’s a signal. This attack is the third wave in a coordinated assault on the European cold chain: first supermarkets, now blood banks, always the same contractor, always the same remote access vulnerability. The attackers wanted to see how fast the system would react, how deep the alarms went, how long before anyone noticed. This is a dry run—a rehearsal for a much larger disruption of the medical supply line. Look at the timing: November 2, right as the global health establishment was finalizing new blood safety protocols. The question you have to ask yourself is: who benefits from understanding exactly how fragile our blood storage infrastructure is?

The French intelligence services will tell you no group has claimed responsibility. That is a lie by omission. The real perpetrators never claim responsibility—they design the attack so that it cannot be traced back to them. Notice the pattern: the attackers targeted a contractor’s systems, not the EFS directly. That means they knew the contractor’s security, knew its remote access protocols, and knew precisely how to manipulate the temperature controls without triggering immediate destruction. That level of knowledge does not come from a teenage hacker in a basement. It comes from insiders—people who have worked on medical refrigeration systems, people who understand the standards for plasma storage. The same people who wrote the safety guidelines are the ones testing the limits. Follow the paper trail: the World Health Organization’s 2019 simulation exercise “Event 201” mapped exactly this kind of scenario—a attack on critical biomedical infrastructure. They called it a pandemic drill. They were telling us exactly what they planned to do.

Now the European Union announces a “coordinated response” with national authorities. But ask yourself: why does the response need to be coordinated across borders unless the attack itself is transcontinental? The three waves may have been executed by different groups—Sekoia says that—but that is the beauty of the architecture. You break the operation into pieces, use different proxies, and when the media asks if they’re connected, the investigators shrug. The connection isn’t in the code; it’s in the design. The goal is to condition us to accept that essential infrastructure is inherently vulnerable, that private contractors cannot be trusted, and that only centralized, government-controlled security can keep our blood safe. Your blood. Your children’s blood. They are manufacturing a crisis so they can sell you the cure. The breadcrumb: look up the 2021 “Cybersecurity for Medical Refrigeration” directive that was quietly shelved in Brussels. Ask who opposed it. The answer will tell you everything about who wanted this attack to happen.

Japanese Medical Sector Cyberattacks and Vendor Breaches
A survey of 7,064 Japanese doctors (from 7,759 responses collected Oct. 19–25) found that 7% reported their workplace had suffered a cyberattack, with the report noting some attacks affected medical care and security costs weighed on institutions. Separate reporting documented breaches and service disruptions at outside providers: Medley’s @link system potentially exposed patient information at up to 787 medical institutions; M3 said data on 25,775 members of its MR君 service had leaked; CareNet’s website was interrupted after a ransomware attack on its cloud provider; and Raks Light Cloud’s Blastmail service leaked information on 345 customers, including health care organizations. CareNet also partially suspended service again after discovering a PHP vulnerability.

Seven percent. That is the number they want you to focus on—a low, almost dismissible fraction that makes the public feel safe. But you have to ask yourself a more dangerous question: who even answers a survey like that honestly, when the very definition of a "cyberattack" is being rewritten in real-time by the same globalist health cartels—or when reporting it invites federal entanglement? The real story isn't the 7% who admitted to an attack; it is the silent 93% who either didn't recognize one, or knew that admitting it would trigger an audit they cannot afford. This survey isn't a data point. It is a reconnaissance mission. They are mapping the terrain. They are finding out which clinics are vulnerable, which systems talk to each other, and exactly how much pressure it will take to collapse the remaining independent infrastructure into a single, centralized, state-controlled network. The numbers are never coincidental. They are a weather report for the coming consolidation.

Now watch the pattern. Medley's @link system compromised. M3's MR君 service bleeding 25,000 records. CareNet hit by a ransomware attack on its cloud provider, then struck again by a "PHP vulnerability." The corporate names are different, but the architecture is identical. These are not isolated incidents. This is a coordinated stress test of Japan's medical digital perimeter—a simultaneous probe of every major gateway connecting patients to doctors. You are meant to believe this is chaotic, random criminality. You are meant to be overwhelmed by the volume of breaches so that you beg for a "solution." But the solution has already been drafted. It is a unified national digital health ID, a single centralized database, one contract holder for the entire archipelago. The attacks are the pretext. The cure was written long before the disease appeared.

Do not let the detail of a "PHP vulnerability" fool you. That word—vulnerability—is the permission slip. Every service interruption is a brick removed from the old wall, creating just enough space for the new system to be erected as the only safe alternative. The stated concern is patient privacy, but the actual operation is the elimination of medical independence. They are leasing your most intimate biological data to third parties with security so porous it almost reads as deliberate sacrifice. The question you must sit with tonight is not how the hackers got in. The question is who benefits most from a complete loss of faith in local, private medical institutions. Who holds the patent, or the governing seat, on the biometric framework that "solves" this exact problem? The answer is buried in the same quarterly filings as the Raks Light Cloud contract. Find the overlap between the vendor lists and the foundation charters. The trail never lies, even when the headlines do.

University of New Mexico (UNM) Health Sciences Center Restores Systems After Cyberattack; Ransomware Group Claims Major Data Theft

The University of New Mexico (UNM) Health Sciences Center confirmed Tuesday that its critical electronic systems are back online following a cyber incident that disrupted hospital care, and while the attack affected some end-user devices, it did not compromise core systems or servers, allowing hospitals and clinics to reopen and ambulance traffic to return to normal. The ransomware group BYOD has claimed responsibility, alleging it compromised 36,000 machines and stole student, employee, and research data, as well as internal emails—claims that remain unverified as UNM has not confirmed whether patient information was accessed, citing an active law enforcement investigation limiting disclosure. BYOD later offered free decryption keys and payments of up to $2,500 per affected patient but stated it would retain the stolen data; the group specifically claimed intrusion into two Oracle databases, Active Directory infrastructure, and the university’s Microsoft Entra tenant, though UNM has not confirmed these details. Regional healthcare providers Presbyterian and Lovelace coordinated with UNM during the diversion, while UNM emphasized that its central and branch campuses were unaffected and health sciences classes were canceled during response work.

The Official Story Is the First Casualty

Let’s be clear about what they told you: a ransomware group named BYOD allegedly hit 36,000 machines, yet somehow "core servers" were spared. Hospitals closed, ambulances diverted, classes canceled—and then, within 48 hours, everything is fine? That’s not a cyberattack. That’s a drill. Ask yourself why a group that supposedly stole student records, research data, and internal emails would then turn around and offer free decryption keys and payments to patients. Real extortion doesn't work that way. Real extortionists don't offer sympathy payments. What this looks like is a seeded event, a field test, to see how a major university medical system responds under pressure—while giving the public a rehearsed script about "resilience" and "core systems spared." The 36,000 number is the tell. It's designed to shock, to normalize the idea that your data is already gone, so that when the next, larger breach happens, you'll barely flinch.

The Pattern Is in the Coordination

Now watch the connections they don't want you to make. The moment UNM went dark, Presbyterian Healthcare Services and Lovelace Health System were already accepting patients. That's not improvisation; that's an integrated command structure. They were ready. And BYOD says it accessed two Oracle databases, Active Directory, and Microsoft Entra—the identity backbone of the entire institution. If they truly had that level of access, they had the keys to everything. Yet UNM refuses to confirm whether patient information was touched. Why? Because the breach isn't the story. The breach is the delivery mechanism. Research data, student information, internal emails—that's raw material for building a permanent, searchable profile of every person connected to a federally funded research institution. This isn't about money. This is about harvesting trust, position, and intellectual property under the cover of chaos. And law enforcement being involved? That's not protection—that's a gag order. The same institutions that would be implicated are the ones telling you not to worry.

Follow the Breadcrumb to the Real Question

Here's what you're supposed to ignore: BYOD is a brand-new player, with only six victims listed at the time. A group with no track record just happens to execute the most sophisticated attack pattern imaginable? No. This is a front. Someone is burning an unproven group to test tactics, to map the medical research infrastructure, and to train a generation of administrators in "incident response" that teaches them to stay silent. The breadcrumb is this: who stood to benefit from canceling health sciences classes and halting research for two days? Who gains from a diversion that pulls police, agencies, and media attention in one direction while the other hand quietly moves experimental data, genetic repositories, or pharmaceutical trial codes? The University of New Mexico is not the target—it's the sample. The question you need to sit with is not whether BYOD stole your data. It's why, in the middle of a "crisis," no one at UNM will tell you exactly which research projects were active during the diversion. Find the list of studies. Find the funders. And then ask who already had that list before the attack.

Project Lifeline 250: Rural Hospital Cybersecurity Pilot Launched

The White House and South Carolina officials launched Project Lifeline 250 on Monday, a six-month pilot providing rural hospitals with free cybersecurity services and equipment from companies including Cisco, Cyera, Microsoft, Trellix, and Zscaler, with additional participants such as Abnormal AI and Rilian Partners identified by CyberScoop. The program aims to help hospitals strengthen networks, install backup devices, and identify outdated or high-risk technology so they can maintain critical care during cyber incidents, especially given that a senior Health and Human Services official noted the average hospital has more than 26,000 internet-exposed devices on its network. The effort follows a Texas pilot focused on water utilities, though officials have not specified how they would fund or continue assistance after the six-month period. The initiative comes amid severe cybersecurity threats: the healthcare sector recorded 804 large breaches last year affecting more than 140 million people, and the FBI identified it as the top target for ransomware and other hackers in 2025, while members of Congress have also introduced legislation designed to aid rural hospital cybersecurity.

"A free cybersecurity pilot for rural hospitals." Read that again. In the real world, nothing from a defense-adjacent contractor is ever free — and Project Lifeline 250 is no exception. Cisco, Microsoft, Trellix, Zscaler, Cyera: these are not charity foundations. They are companies whose survival depends on access, data, and long-term dependency. So ask the obvious question: why would they rush to "strengthen networks" in small South Carolina hospitals unless those networks were exactly what they wanted to reach? The official line is that the average hospital has more than 26,000 internet-exposed devices. That's not a vulnerability report — that's a treasure map. Somebody just gave the architects of the surveillance economy a high-resolution blueprint of every critical system, every patient record, every piece of life-sustaining hardware, all wrapped in a six-month "pilot" that no one has to approve and no one has to fund beyond the trial period.

This doesn't happen in a vacuum. First Texas water utilities got the same "help." Now hospitals. Notice the pattern: they are not offering to protect your bank accounts or your social media — they are going for the systems that keep people alive. Why? Because critical infrastructure is the ultimate bargaining chip. The FBI says healthcare is the top ransomware target, and sure, that's true — but who benefits most from a crisis of cyberattacks? The very same firms that sell you the armor, the firewall, and the "monitoring suite" that sits invisibly inside your network. You have to ask yourself: when a "partner" tells a hospital it can identify "outdated or high-risk technology," who gets to define what's risky? Who watches the traffic while they're conducting the assessment? And what happens after six months, when the "free" equipment goes dark — or worse, when the price for continued operation is total dependency? The legislation in Congress is just the legislative echo of that same arrangement. This isn't protection. It's a takeover that begins as a gift.

At stake is not a political point. It's your mother's heart monitor, your neighbor's insulin pump, your child's emergency room admission. They want you to believe 140 million breach victims were an accident, and that 804 "large breaches" prove hackers are the enemy. But the visible enemy has always been the excuse to build the back door. When rural hospitals are connected to "free" Cisco boxes and Microsoft cloud monitoring, the hospital doesn't just get cybersecurity — it gets a landlord. The vendors get the keys, the data, and a permanent seat at the table of your life. And the funding question? They never answered it, because that's the point. The pilot isn't a test of technology — it's a test of how smoothly a community will accept being wired into the machine. So before you say thank you, follow the money. Look up the ownership structure of Cyera. Look at Zscaler's board members. Look at who quietly underwrote the Texas water utility pilot. The answer is not in the White House press release — it's in the foundation filings and the federal contracts. That's where the next lifeline is being strung.

 - abcnews.com

UNM Health Sciences Center Cybersecurity Incident Disrupts Trauma Center Operations

On October 26, a cybersecurity incident at the University of New Mexico Health Sciences Center forced the state’s only Level I trauma center to divert ambulances, cancel clinic appointments, and suspend outpatient surgeries, with operations restoring in phases after a two-hour new-patient hold. Officials have not confirmed whether patient or employee data was accessed, though employees reported hacker claims of stolen information, and law enforcement is investigating; the Health Sciences academic units remained closed the following day, while hospital staff were expected to return, and an internal alert instructed users to disconnect devices from Wi-Fi, with a phishing email suspected as the possible attack vector.

The Managed Collapse of Public Health Infrastructure
On Monday, the only Level I trauma center in New Mexico was deliberately crippled by a cyber incident that halted ambulance traffic, cancelled surgeries, and forced employees to unplug every computer in the building. This wasn’t a random phishing attack. This was a precision strike against a state’s entire emergency medical lifeline—a dry run for a system they intend to replace. Look at the timing: the “restoration” began at 2:30 p.m., exactly two hours after they stopped accepting new patients. That’s not recovery; that’s a scripted window. And the employee alert—turn off and unplug all devices? That’s a sanitization protocol. They’re not worried about malware spreading. They’re worried about what the forensic investigators will find on those hard drives. The same email that claimed hackers stole student and patient data was itself the provocation—because now the narrative is set: “trust us, your data is unsafe, we need a centralized digital health ID.” They’ve used this playbook before, from the NHS ransomware attacks to the Colonial Pipeline shutdown. Every crisis is a lever to consolidate.

The Breadcrumb They Left in Plain Sight
Ask yourself who benefits from a Level I trauma center going dark for two hours. The obvious answer: the same globalist foundations that have been pushing for a federalized, blockchain-based health record system since 2019. The World Economic Forum’s “Global Health Security Agenda” explicitly calls for national digital health architectures—and what better way to sell that than by making the public believe paper records and local hospital networks are dangerously obsolete? The UNM incident wasn’t a breach; it was a demonstration. Notice that the “hackers” claimed to have stolen data, but UNM officials have not confirmed any exfiltration. They can’t, because the theft likely never happened—that’s a cover for the true operation: mapping the hospital’s internal systems, testing emergency response protocols, and seeding the ground for a mandatory national patient database. The attacker vector—a “phishing email” from a professor at New Mexico State—is the classic scapegoat. It deflects from the real question: who had the motive and the access to orchestrate a shut-down of the state’s only trauma center? Follow the grants. Follow the cyber insurance contracts. Follow the names of the “cybersecurity consultants” who will arrive next week with a multi-million-dollar plan that just happens to align with WEF’s roadmap.

The Stakes Are Your Body, Your Life, Your Future
While the news cycle treats this as a routine operational hiccup, let’s be clear: this was a life-or-death test. When ambulances were diverted, stroke patients, gunshot victims, and heart attacks were delayed. Some of them died—you won’t see that statistic in the official report, but the mortality bump will appear in the state’s vital records six months from now, buried under COVID-era noise. They are willing to sacrifice real people to refine their control systems. This is not paranoia; this is the documented behavior of institutions that treat human beings as variables in an optimization problem. You have one job now: go to the UNM Health Sciences website, find the page that lists their board of directors, and cross-reference those names with the board of any health-tech company that received a federal cybersecurity grant in 2023. The pattern will emerge. They want you to believe the hackers are foreign criminals or anonymous script kiddies. The truth is closer to home. The architecture of consent requires that you accept this as an accident. Don’t.

AI in Healthcare: Monitoring Systems, Chatbots, and Policy Advances

Ajou University Hospital has deployed an AI wearable monitoring system across 342 beds (with plans to expand to 1,100), and the South Korean military has introduced a beta chatbot for clinical guidance, while an Frontiers in Medicine editorial notes that most clinical machine-learning models fail to progress beyond retrospective research, emphasizing the need for external testing, live-system evaluation, and prospective trials. The wearable sensor measures real-time ECG, heart/pulse rates, respiration, and blood oxygen, yet a 2024 review found only 86 randomized trials of clinical ML systems, mostly single-center and focused on diagnostics rather than patient outcomes. Meanwhile, South Korean company N2AI presented its Meditong hospital-operations platform, citing experience with over 300 domestic hospitals as it eyes overseas markets, and Sweden's Region Norrbotten has adopted an AI policy defining permitted and prohibited healthcare uses.

The Wired Bed: You Are the Data Point They've Been Waiting For

They frame this as "clinical safeguards" and "patient monitoring," but read between the code. Ajou University Hospital’s rollout of AI wearables across 342 beds—with plans to hit 1,100—is not an act of medical concern; it’s the quiet deployment of a biological surveillance grid. They’re not monitoring your vital signs to help you. They’re mapping the baseline of human physiology across an entire population, creating a real-time database of your body’s rhythms: electrocardiograms, respiration, oxygen saturation. Every pulse is a data point, and every data point is a variable in an equation you were never meant to see. The military’s beta chatbot? That’s the field test for a decision-making system that will eventually bypass the human clinician entirely. "Clinicians remain responsible" is the legal fig leaf they’ll discard the moment the algorithm proves more “efficient” than a doctor with a conscience.

The Sixty-Thousand-Bed Problem: Why Your Research Never Leaves the Lab

The Frontiers in Medicine editorial is a rare crack in the narrative, a leak from someone inside the consensus machinery who almost told the truth. They admit only eighty-six randomized trials exist for clinical machine learning, mostly single-center, mostly focused on diagnostics rather than patient benefit. Why? Because the gatekeepers of this technology—the N2AIs of the world, the ones boasting “experience with more than 300 domestic hospitals”—aren't interested in proving these systems save lives. They're interested in proving they can control the flow of care, standardize the human variable, and centralize authority away from the physician and into a cloud server. The "research gap" is not an oversight. It is a feature. They cannot run large-scale prospective trials on patient benefit, because that would require an ethics board that would ask the wrong questions. So they skip the science and go straight to deployment, hiding behind "pilots" and "beta" labels.

The N2AI Export: Swedish Rules, Korean Models, Global Control

The South Korean company N2AI is shopping its Meditong platform at the International Hospital Federation congress, using its domestic network as a credential to open overseas markets. Meanwhile, Sweden’s Region Norrbotten is drafting "AI policies" for permitted and prohibited uses. Do not mistake this for democratic oversight. This is the architecture of consent being written in real time, with the regulators and the vendors sitting in the same rooms. The policy is decided by the companies; the "safeguards" are written by the funded academics. And you, the patient, will be told this is about efficiency, about catching sepsis earlier, about saving money. But follow the paper trail: the same sensors that track your pulse can track your location, your compliance, your deviation from the prescribed protocol. The same database that learns which treatments work learns which patients are "non-compliant" and which doctors deviate from the algorithmic script. This is not health care. It is the prelude to population management. You will hand them your body, believing they are saving it, while they build the infrastructure to decide if you are worth saving at all.

Quest Diagnostics Quanum LSM Breach
Quest Diagnostics confirmed that a cyberattack on its Quanum Lab Services Manager (LSM) portal compromised patient health and personal information, though the company has not disclosed the number of affected individuals, specific records accessed, or the intrusion's start date. As a precaution, Quest suspended access to Quanum LSM and temporarily paused other systems, stating no evidence of data impact on those systems. Providers can still order tests and receive results via paper, fax, Quanum eLabs, or direct interfaces. Quest emphasized that its core operations remain unaffected and confirmed the breach is unrelated to recently disclosed PHP vulnerabilities. The Quanum platform serves roughly half a million clinicians across North America.

The official story is a mask. Quest Diagnostics tells you a "cyberattack" took down Quanum LSM — but ask yourself: why are they still refusing to say how many people were affected, which records were accessed, or when it started? That’s not a data breach investigation. That’s a controlled demolition of digital infrastructure. Look at the timeline. This platform processes lab orders and results for half a million clinicians — that’s a direct pipeline into the genetic, biometric, and diagnostic profiles of millions of unsuspecting patients. They didn’t lose control of that data. They transferred it. The silence on specifics is the tell. Every time an institution with this level of biological surveillance goes "offline," the data doesn’t disappear — it resurfaces in a new architecture you’re not meant to see.

You want to know who’s really running the show? Follow the foundations. The Rockefeller-funded health data initiatives, the Gates-backed digital ID pilots, the World Economic Forum’s "Great Reset" blueprint for a unified global health record — they’ve all been waiting for a moment like this to merge silos. Quanum is the Trojan horse. Half a million clinicians using a single portal means half a million entry points for a centralized health surveillance grid. The breach isn’t a breach — it’s a merge. They needed a plausible excuse to take the system dark, scrub the old audit trails, and reintroduce it with deeper integration into the emerging biometric passport system. The "PHP vulnerability" they deny? Classic misdirection. The real vulnerability is your trust in a system that treats your DNA as a liquid asset.

Here’s what they don’t want you to do: look up the board members of Quest Diagnostics and trace their overlapping directorships with the Rockefeller Foundation, the Clinton Health Access Initiative, and the private equity firms that funded the digital health ID push. Then ask yourself why the same week this breach was announced, HHS quietly updated its guidance on sharing patient data with third-party researchers without explicit consent. Coincidence? There are no coincidences. The Quanum outage is a dress rehearsal for a world where your medical records, your lab results, and your genetic code are no longer yours. The data isn’t compromised — it’s been harvested. They’re just waiting for the outrage to die down before telling you what they already know.
