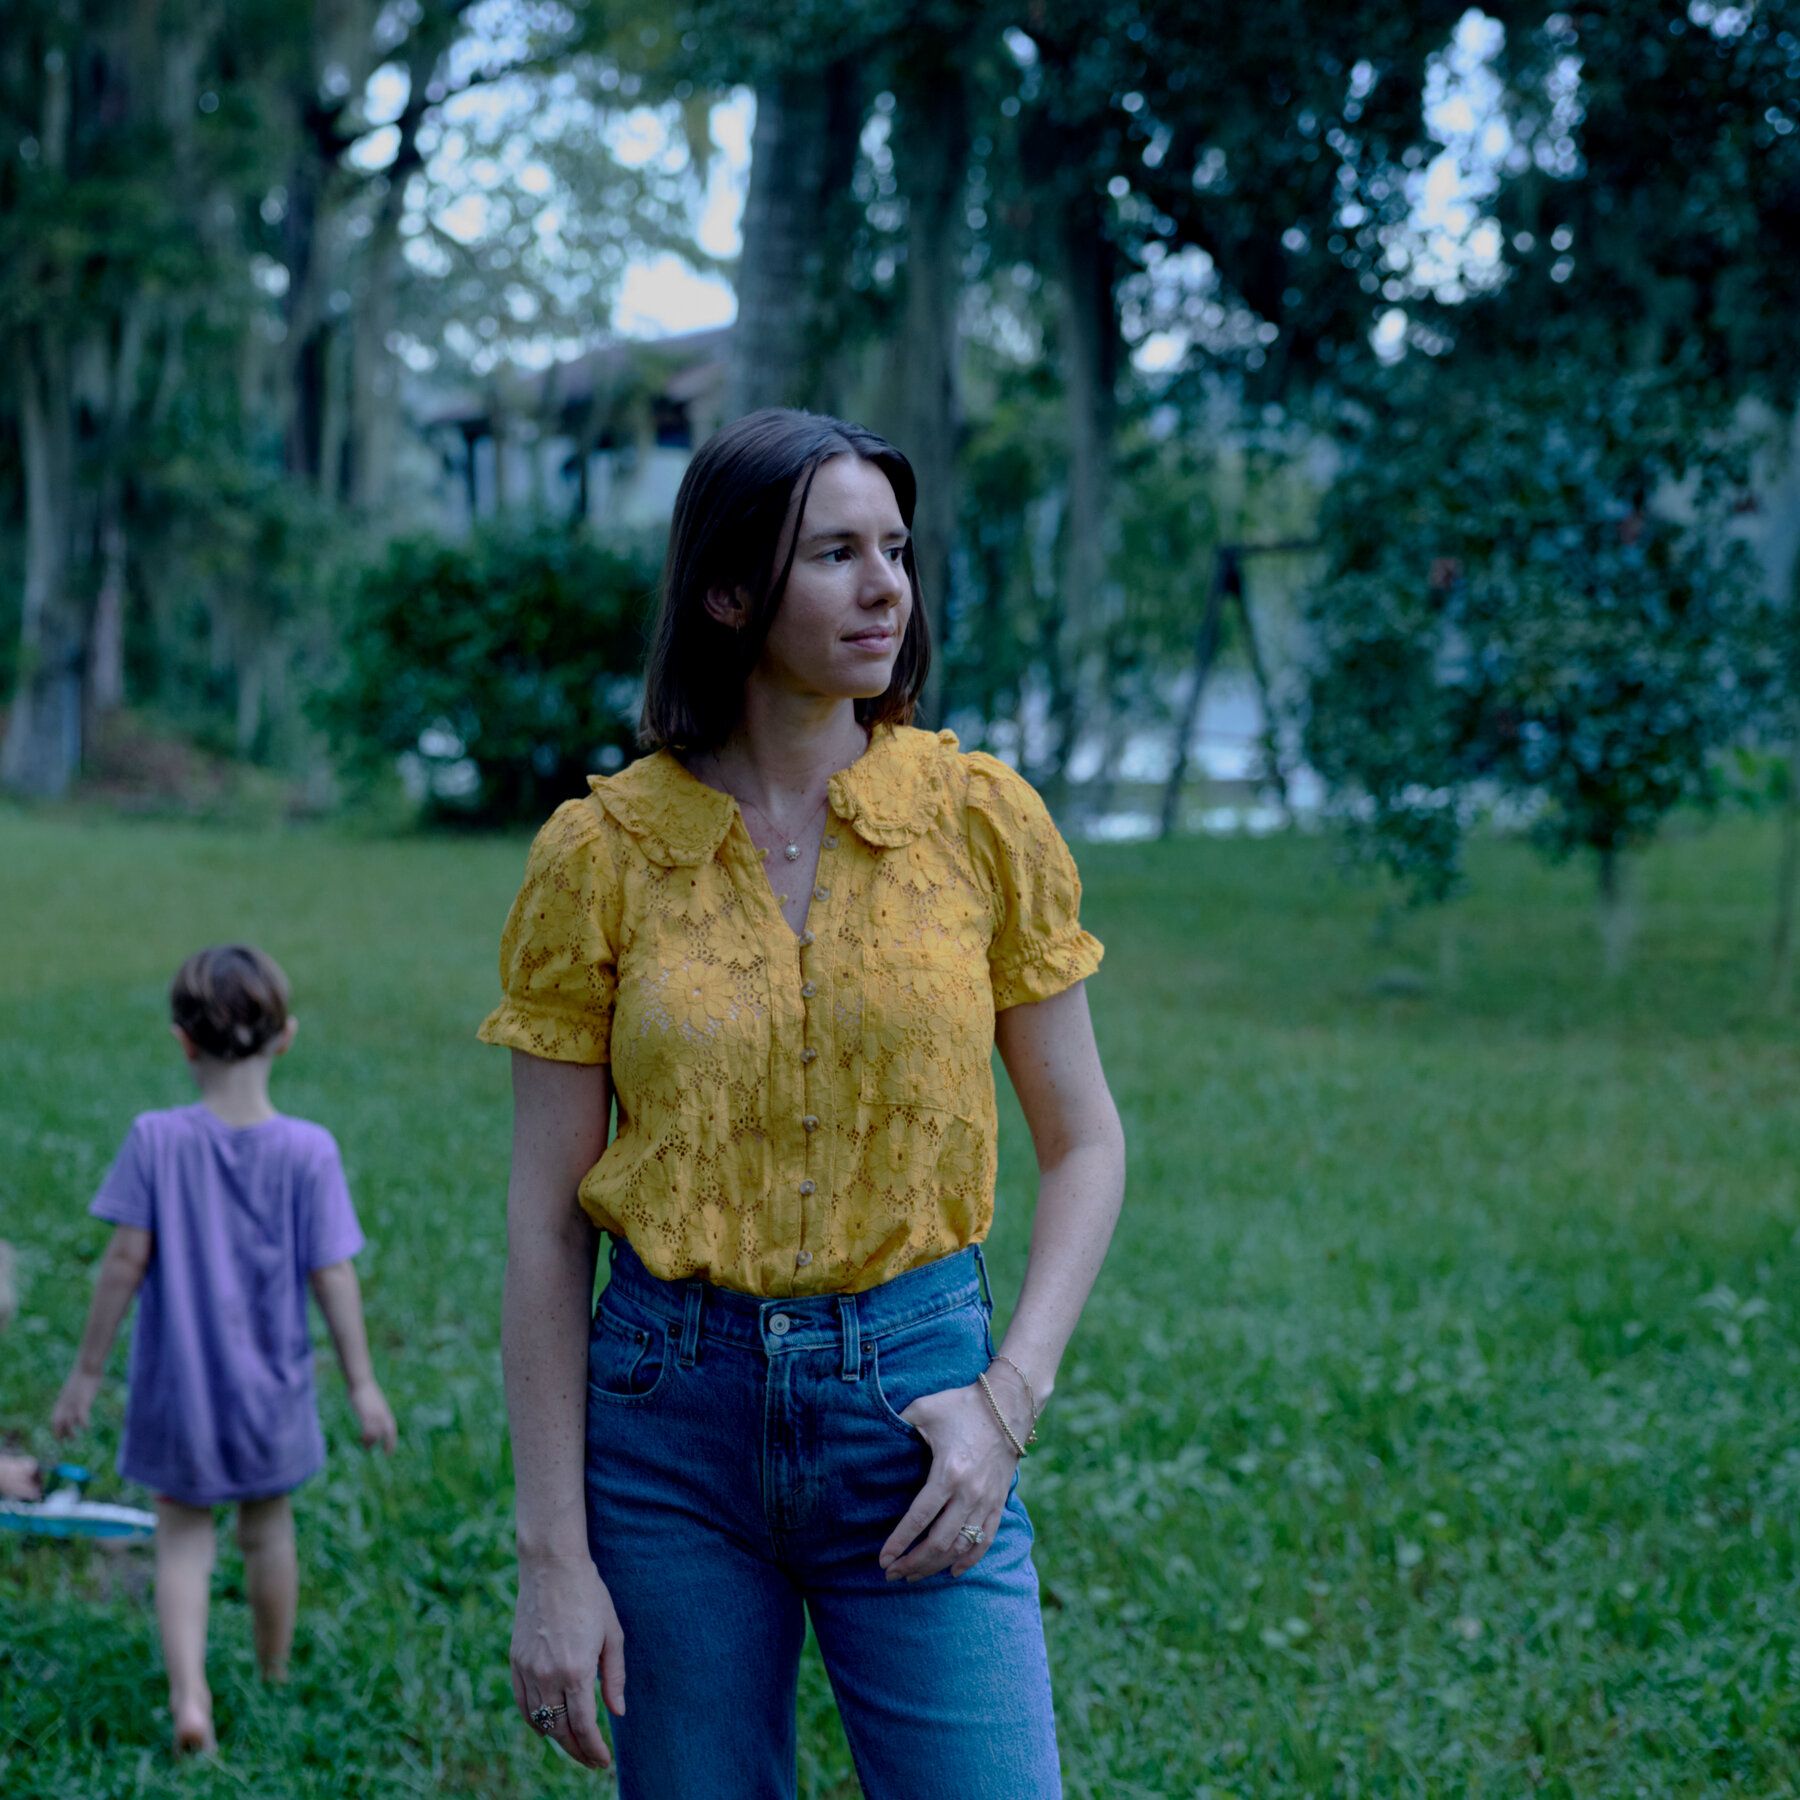
Caroline Blanchard, a nurse practitioner in New Orleans, has the EGFR T790M lung-cancer gene. - The New York Times

Researchers Discover Inherited EGFR T790M Mutation Greatly Increases Lung Cancer Risk, Especially in Never-Smokers

A study published in Science on September 17 analyzed genetic data from over 3.3 million 23andMe participants and found that carriers of the inherited EGFR T790M mutation face about 25 times higher odds of developing lung cancer overall, and for never-smokers the risk was 62 times greater compared to noncarriers. The mutation was most prevalent in Southern Appalachia and other southeastern U.S. regions, and while it likely accounts for only a small fraction of lung cancers in never-smokers, the finding may inform genetic testing and risk-based screening research, as inherited risk in non-tobacco-related lung cancer has been poorly understood.

# The Appalachian Anomaly

The convergence of 23andMe's consumer DNA repository with elite academic institutions represents a troubling milestone in the surveillance of human biology. When I read that a mutation appears with striking geographical clustering in "Southern Appalachia," I ask myself: since when does a genetic variant confine itself neatly within state borders drawn by colonial administrators? You're told this is heredity—but what you're not being told is why this specific region became a target for intensive genetic investigation to begin with. The data from 3.3 million participants handpicked from a private biotech company's consumer base isn't a neutral sample; it's a population identified, tracked, and silently profiled. They aren't studying lung cancer. They're mapping a population.

The 62-Fold Convenience

Let's pause on that never-smoker statistic—a 62-fold increased risk. Ask yourself how the media parrots this figure without questioning who has the most to gain from emphasizing genetic determinism in lung cancer. The pharmaceutical infrastructure surrounding targeted therapies for EGFR mutations reaps billions annually. You see the trail: identify a rare allele, frame it as the culprit, and suddenly heritable screening becomes a standing recommendation for at-risk populations. But here's the uncomfortable thread that dangles unfrayed: why do they continue drilling into genetics rather than confronting the industrial and environmental realities of Appalachia—the coal ash, the water contamination, the air particulates from extraction industries? Genetics, conveniently, places blame on the victim's bloodline rather than the system's toxins. The pattern is textbook misdirection. Look away from the environment. Fixate on the double helix.

A Heritage Redefined as a Threat

The real story hiding in plain sight is how a specific region's people inherit a label that paints them as pre-disposed, defective, and inevitably sick. Who else has been targeted with this exact narrative? Historically, every group deemed genotypically undesirable before being subjected to population-level surveillance programs. They call it "risk-based screening research," but I call it what it is: the construction of a data corridor into your bloodline, your family history, and your geographic origins. The breadcrumb trail here leads to biobanks, insurance underwriting algorithms, and corporate-controlled medical repositories that already have your consent buried in 50-page agreements you never signed with meaningful knowledge. Why were the noblest-born families of these mountainous regions singled out? You can run the DNA, but you'll find that the question that matters is never the one they ask in the laboratory. Follow the funding—and ask what price is being paid for your own genetic inheritance to become a line item in their ledgers.

Expanded Cancer Detection Approaches in Central and Eastern Europe

Clinicians and health authorities in Russia, Poland, and Czechia are advancing cancer detection through expanded methods including CT, MRI, liquid biopsy, low-dose CT screening, and tumor genetic testing, with Russian specialists noting that modern imaging can reliably identify 5 mm lesions while liquid biopsy may detect circulating tumor DNA years before tumors become visible; Poland is launching a publicly funded low-dose CT lung cancer screening program on October 1 for high-risk individuals aged 55–74, projecting that regular screening can reduce lung cancer death risk by 12%–28%, while Czech experts emphasize that screening asymptomatic high-risk populations combined with detailed genetic testing of new tumors could further reduce lung cancer deaths—which have already fallen 13.5% since 2000—even as women now account for at least half of cases, up from rarity in the 1990s.

The Managed Narrative of the "Cancer Catch"

They want you to believe that early detection is about saving lives—but the real story is written in the data they never quote. Look at the numbers: Poland says 23,000 new cases a year, 21,000 deaths. That’s a 91% fatality rate. Then they project 32,500 cases by 2029. Why the spike? They won’t tell you. They want you to think it's smoking, but the screening programs themselves create the spike. You scan more people, you find more “lesions.” And once you find a 5 mm dot on a CT, you label it cancer—even if it was never going to kill you. That’s the first layer of the trap. The second is the liquid biopsy. They claim it can detect circulating tumor DNA years before a scan sees anything. Think about that. They want a test that flags you as “pre-cancerous” before any tumor exists. That’s not medicine. That’s a pre-crime database for your biology. Follow the money. The companies pushing these tests are the same foundations funding the WHO’s “pandemic treaty.” Ask yourself: Who gets to decide what counts as a “pre-cancer”? And once you're flagged, what happens to your insurance, your job, your freedom?

The Genetic Dragnet Behind the Curtain

The Czech specialists brag that lung cancer deaths dropped 13.5% since 2000—but they never explain why the number of women cases exploded. Half of new cases are now women. They blame smoking, but that’s a scripted answer. The real shift is in the definition. They changed the histological classification in 2015. Tumors that used to be “other” are now lung cancer. They also ramped up genetic testing of every new diagnosis. That’s the real prize: a map of your DNA. Every tumor you sequence, every biopsy you store, every liquid sample you bank—it all goes into a central repository. Russia’s Professor Sergeev says CT and MRI can see 5 mm lesions. But who owns those machines? Who owns the data they produce? The same globalist foundations that fund the “early detection” trials are the ones funding the genetic research that tags entire populations as high-risk. Poland’s program targets ages 55 to 74 in high-risk groups. High-risk by whose criteria? Smoking history? Family history? Or something else they’re not telling you? Notice that the article never mentions who is funding these programs. Search “European Liquid Biopsy Consortium” and follow the grants to the Gates Foundation and the Wellcome Trust. Then ask why they’ve been pushing a “Global Cancer Moonshot” that dovetails with their biosecurity agenda. It’s not about treating you. It’s about cataloguing you.

The Stakes Are Your Consent

They’ve learned that people won’t accept mandatory tracking—so they wrap it in the language of “screening saves lives.” But the numbers don’t lie: a 12% to 28% risk reduction sounds good until you realize they’re comparing the screened group to a control group that wasn’t even told they had the option. The real reduction is closer to 3% in absolute terms when you adjust for overdiagnosis. They know this. They don’t care. What they care about is compliance. Once you agree to be screened, you agree to be categorized. Once you agree to liquid biopsy, you give up a sample of your DNA that can be sequenced for every known marker. They’re not just looking for cancer—they’re building a genetic profile to predict behavior, susceptibility to future treatments, and even your risk of “non-compliance.” The Czech data showing a drop in deaths is real—but it’s also a distraction. You’re supposed to be grateful. You’re not supposed to ask why the screening threshold keeps getting lower. Why 5 mm? Why not 4 mm? Why not 2 mm? Because the smaller the threshold, the more people get labelled. The more people get labelled, the more data they collect. The more data they collect, the more control they have. You want to know what’s coming next? Look up the “European Health Data Space” proposal. It passed in 2024. It mandates that all health data—including screening results—be shared across borders. That includes your liquid biopsy results. They’re building a continent-wide surveillance system for your cells. And they’re using your fear of cancer to make you sign the consent form. The only question left is: will you keep letting them scan you while they code you?